Ebola spreads ‘like wildfire’ as health workers battle exhaustion

Work starts around 5:30 a.m. for Abdou Sebushishe. As he drinks his morning coffee, Sebushishe, who helps lead frontline emergency operations for the International Medical Corps, checks on his teams scattered across eastern Democratic Republic of Congo, where they’re working on the response to the country’s Ebola outbreak.
By 8 a.m., he’s at a treatment centre in Bunia checking on patients, staff and supplies. His afternoons disappear into meetings and operational problems, and work can continue until 9 p.m., when he finally eats what’s often his only meal of the day.
Sebushishe’s long days point to one of the central problems in confronting Congo’s Ebola response: there are only so many experienced people to go around.
When cases are reported somewhere new, that location has to be staffed with a new team. Sebushishe worries about colleagues who are already exhausted, including engineers building treatment centres “day and night”, and healthcare workers working punishing shifts in the face of trauma and loss.
Read: Ebola spreads to seventh Congo province after long-distance trip
“The numbers that you are seeing being reported every day, these are real people,” he said.
Twenty weeks into the outbreak, health workers have managed to tamp down some of the early hotspots. But the virus is still spreading.
What began in three health zones in one province has expanded to 64 across seven provinces.
That widening footprint is putting further strain on a humanitarian response weakened by major aid cuts. Each new front requires surveillance, community workers, infection-control teams and treatment capacity, often in places struggling with conflict, displacement and weak health services.
The longer responders take to get ahead of the virus in new locations, the greater the risk that Ebola crosses Congo’s porous borders – forcing stretched teams to fight it on yet another front.
“You have no impression really that we’re catching up,” said Johnny Falconer, who until recently ran medical care at an 80-bed Ebola treatment centre operated by Médecins Sans Frontières in Bunia. “We’re still dramatically behind.”
Read: Ebola outbreak becomes Congo’s deadliest as UN warns virus is ‘winning’
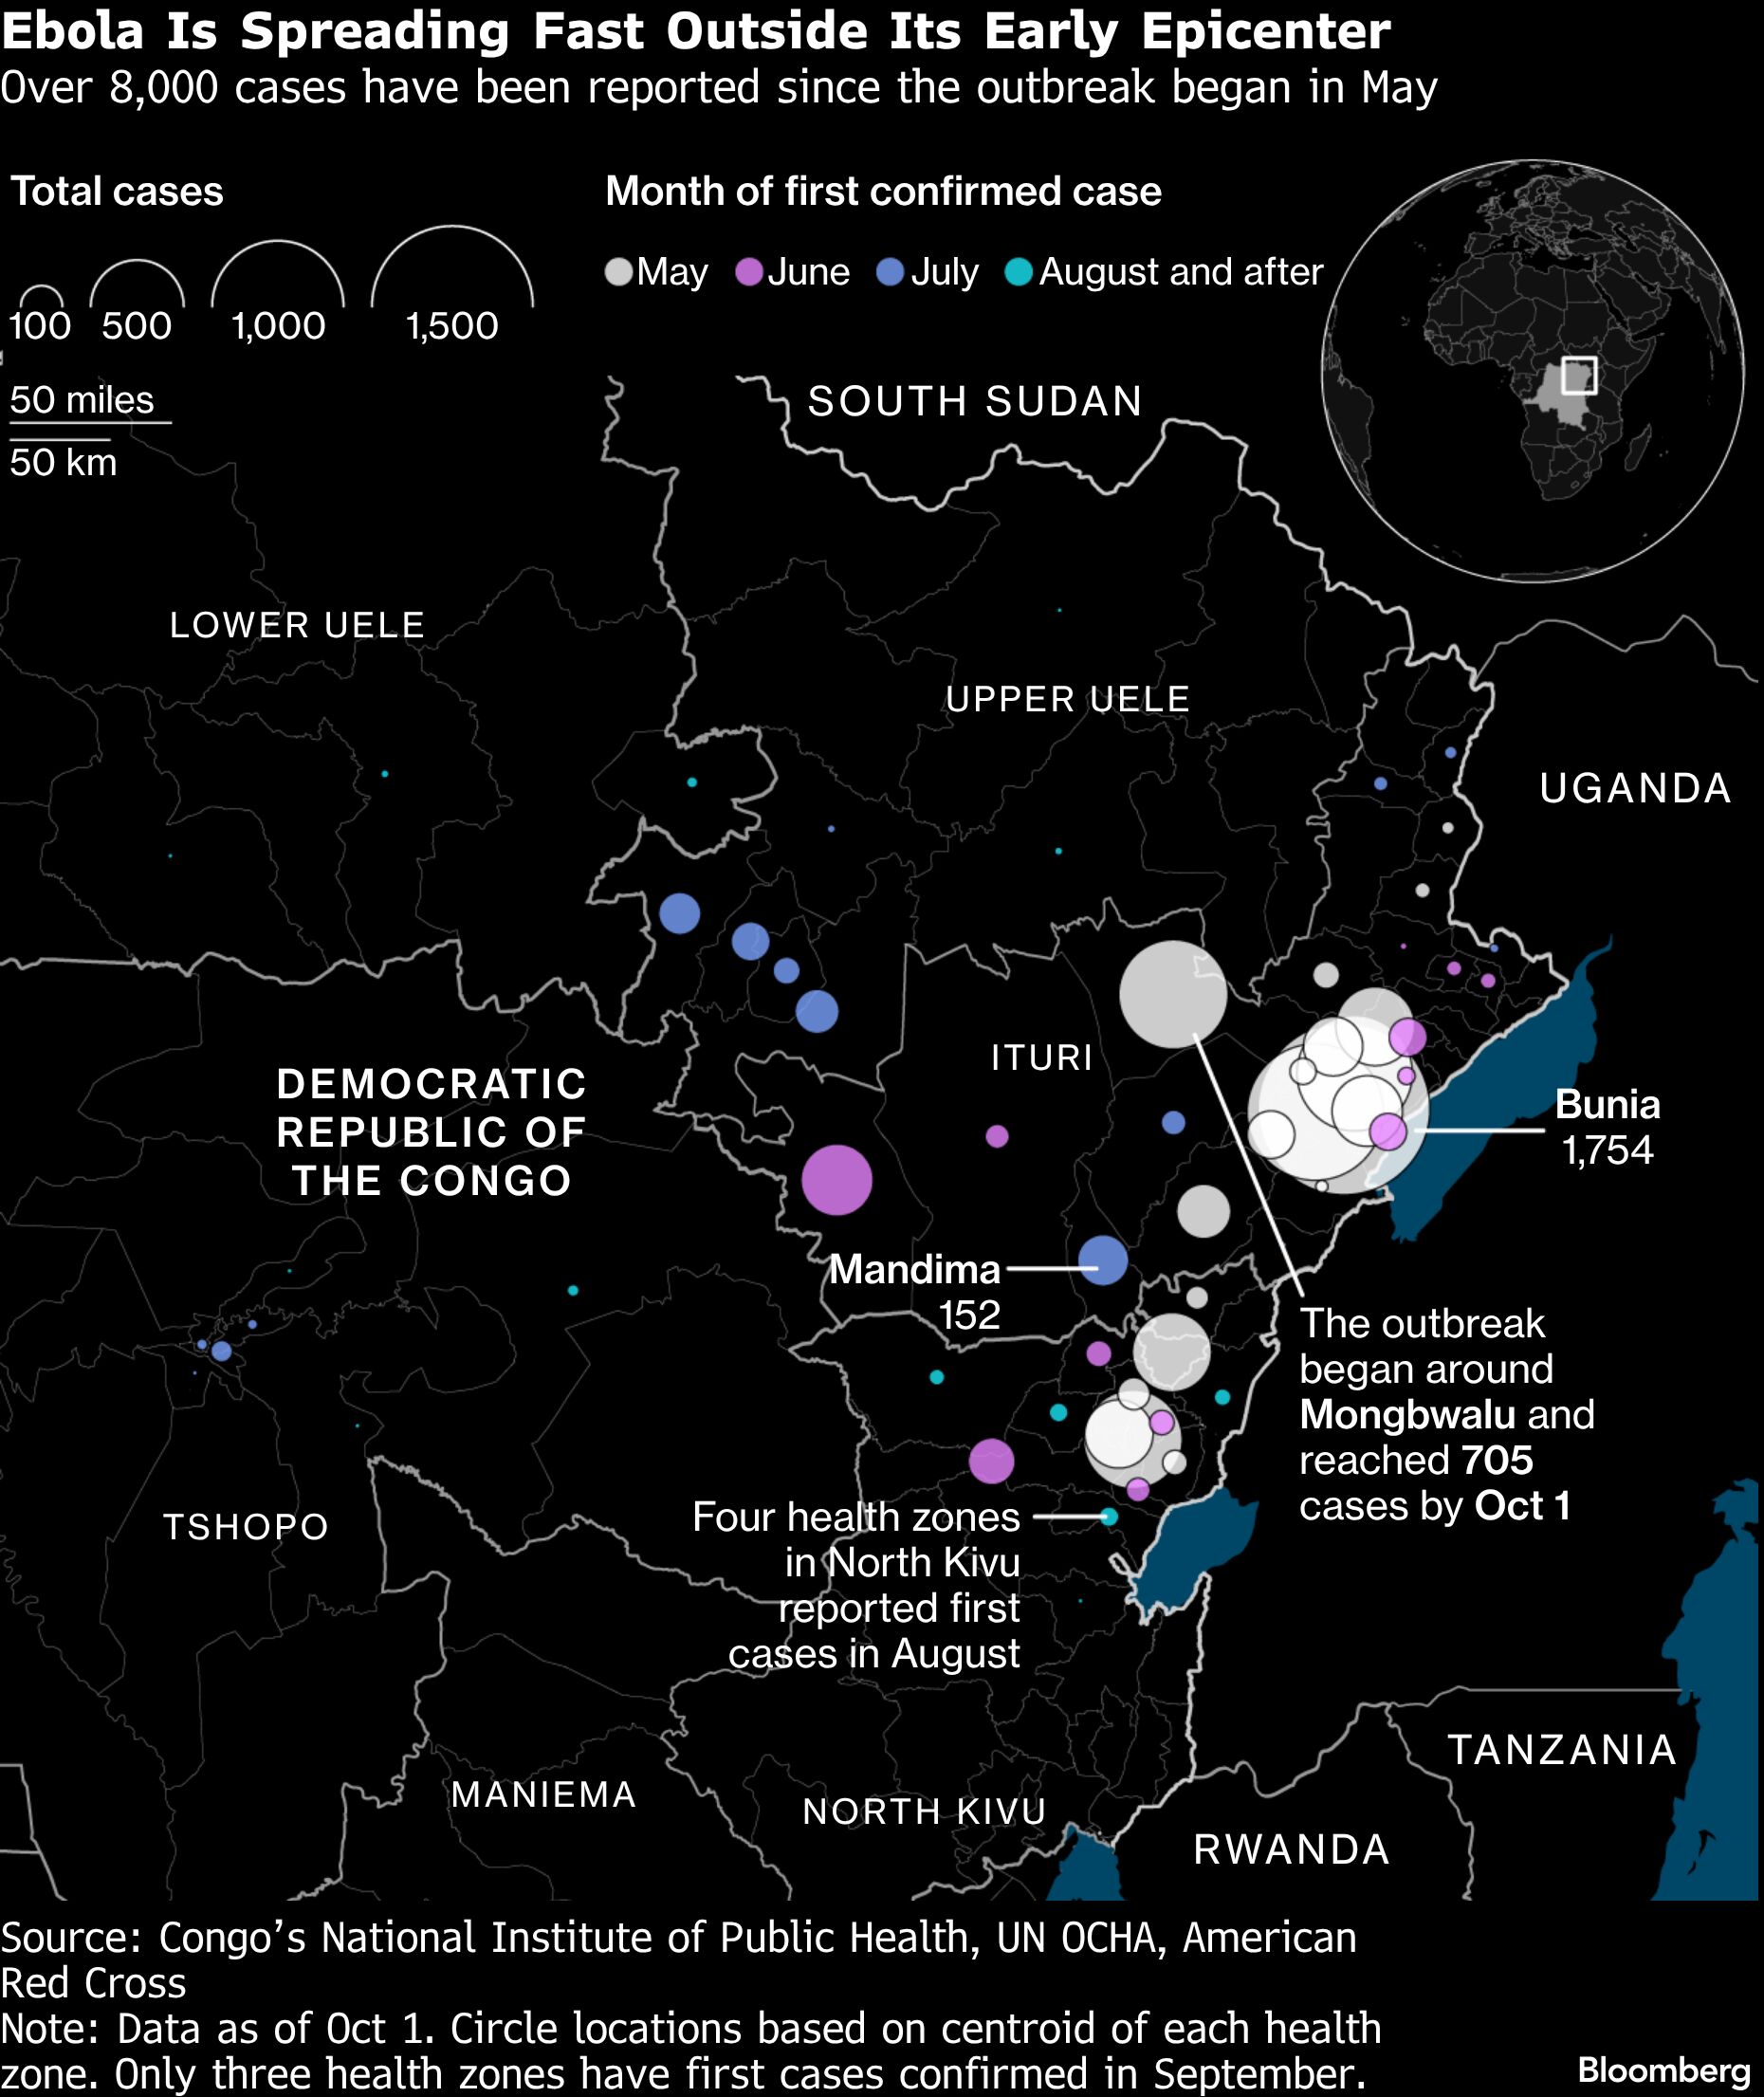
The Ebola outbreak emerged in early May. Reports of unusual deaths around Mongbwalu, a mining town in Ituri, led to an investigation. Standard field tests for the more common Ebola Zaire didn’t detect anything, but samples sent more than 1 100 miles to Kinshasa showed that the virus was a rare species, Bundibugyo.
By the time that was confirmed on 15 May, evidence suggested that the virus had been circulating for weeks. Later investigations indicated the outbreak may have begun months earlier.
Years of conflict and inadequate healthcare in the region have eroded people’s trust in authorities. The sudden arrival of medical teams taking patients into isolation – as well as an old “Ebola business” narrative that claimed some people were profiting from the epidemic – fuelled suspicion.
Frightened families hid the sick, patients fled treatment and burial teams were attacked.
Read: Congo escalates Ebola response as record outbreak spreads
Since then, thousands of healthcare workers have been trained, treatment and testing capacity has expanded and community teams have gone door-to-door looking for infections.
Weekly reported cases have fallen by more than half in Ituri since mid-August, suggesting the response is gaining ground there. But progress is uneven: on 26 September, Mandima, a village about 100 miles from where the outbreak began, reported 25 new infections, including 20 people who had already died in the community.
Less than a week later, its confirmed caseload had climbed to 152 from 118.
Ebola can reach a new community far faster than responders can react. It takes about three weeks to build an Ebola treatment centre to standard. Staffing one can require about 300 health workers, the World Health Organisation (WHO) said.
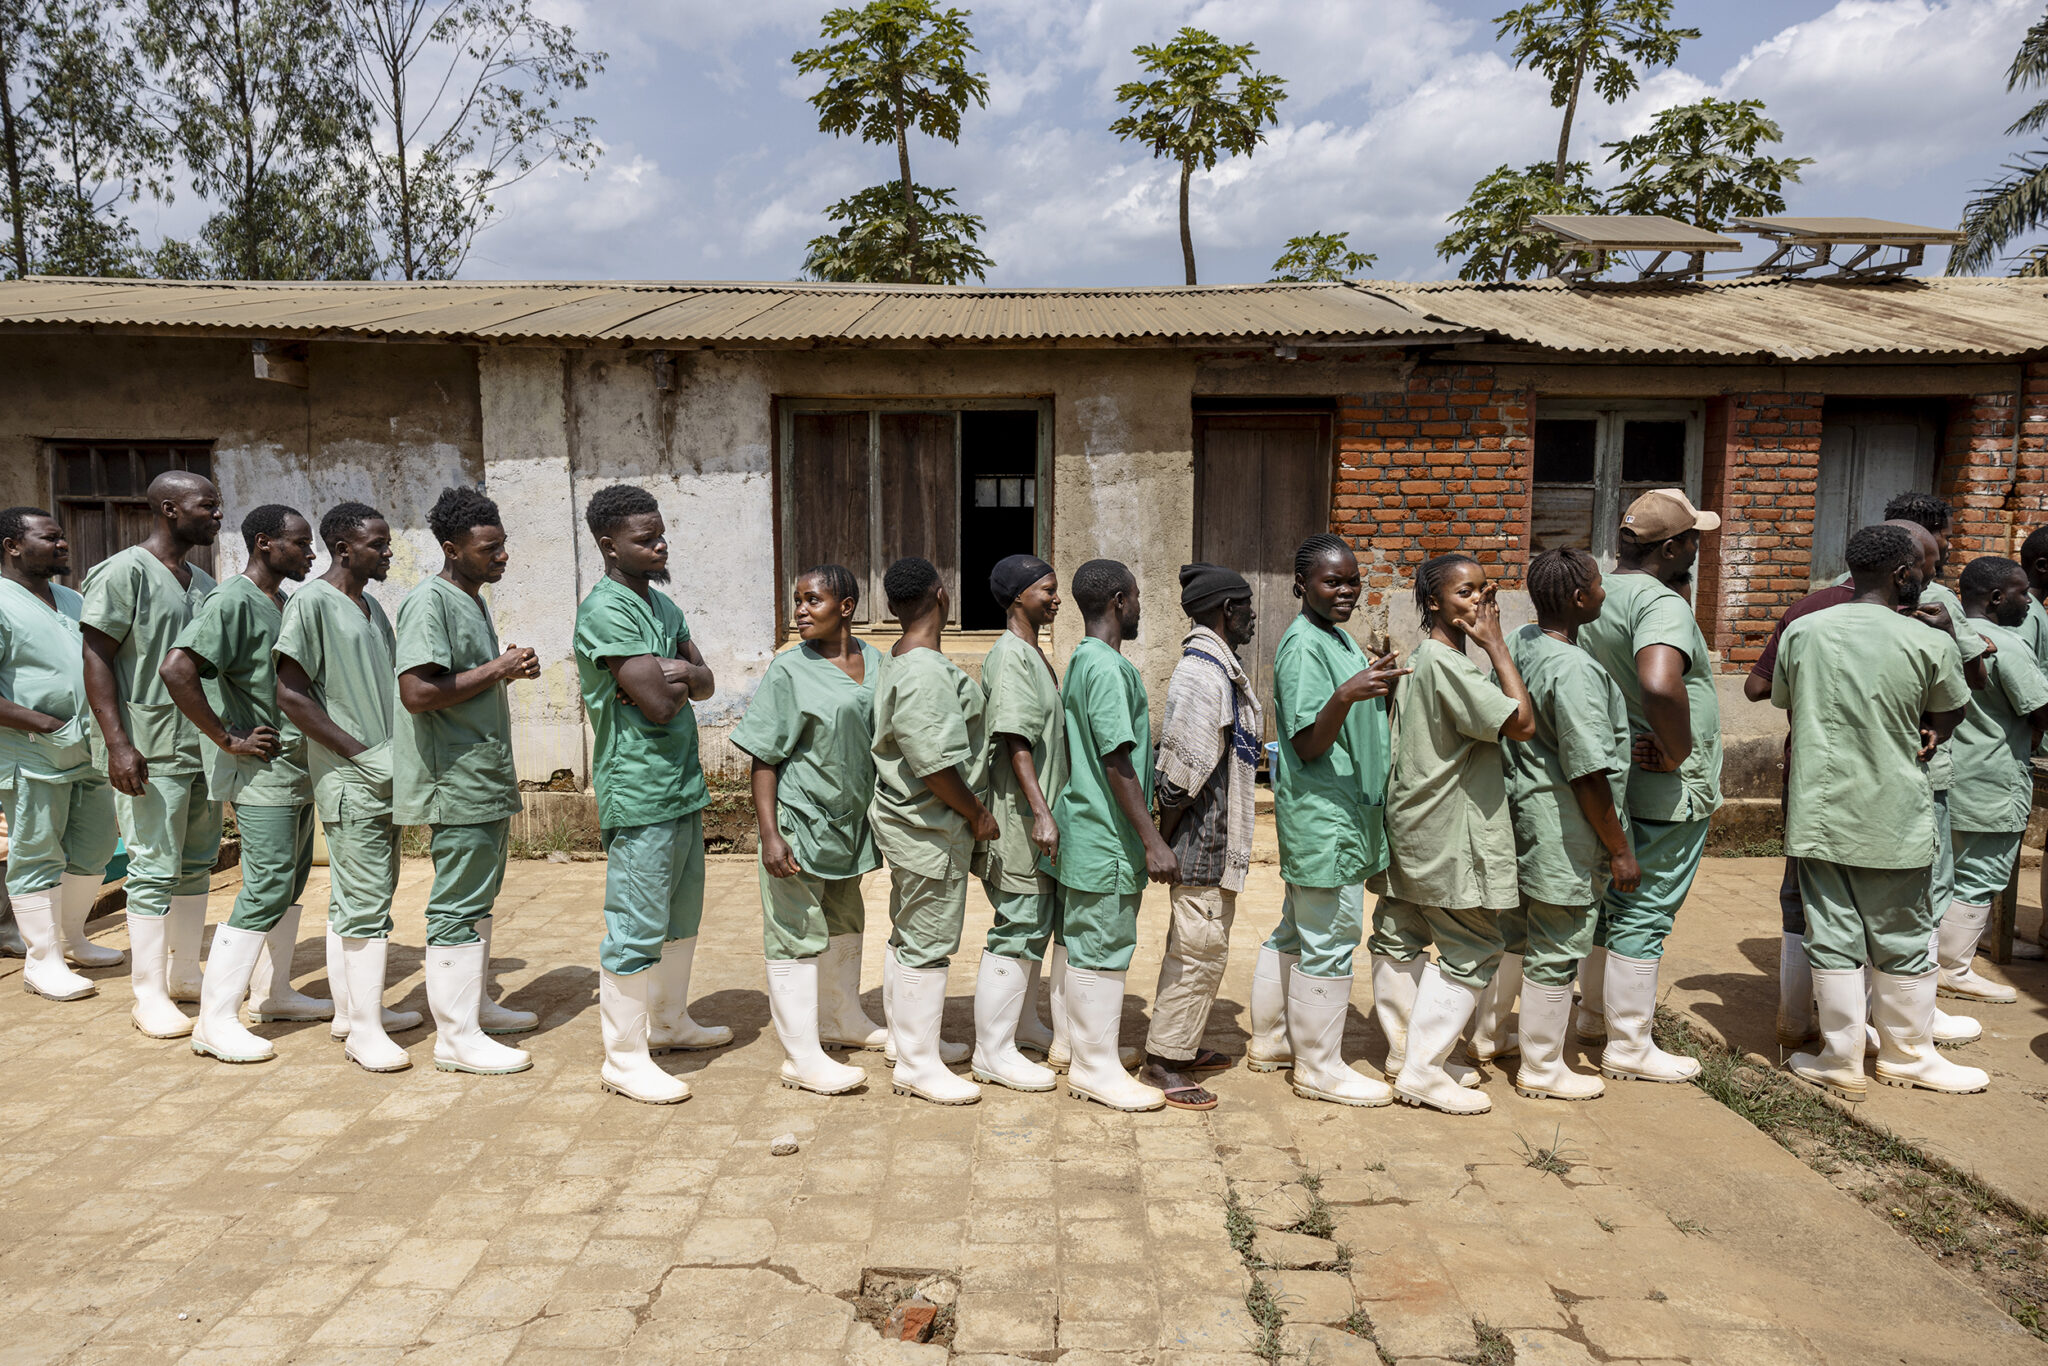
Aid group Samaritan’s Purse runs two treatment centres in Congo. In each, there are two types of patients, those with suspected Ebola and those confirmed to have the virus. It’s critical to prevent cross contamination between them, so each patient is isolated in their own room, which includes piped water to shower and drink.
Chlorine is also piped throughout the facility. Families need to see that patients are not just brought to an Ebola centre to die, said Shannon Hamilton – who recently returned from Congo, where she worked with Samaritan’s Purse – so rooms are fitted with windows to allow patients to see and speak with their loved ones.
Read: Why Congo’s record Ebola outbreak is becoming deadlier
There is what’s called a donning room, which is where staff go through the laborious process of putting on their personal protective equipment. Usually less than an hour later, that health care worker needs to enter the doffing or decontamination area to take their gear off.
“Being in that PPE, you lose about one or two lighters of sweat an hour in these environments,” Hamilton said. “So you can only safely stay in PPE for a short period of time.”
As important as caring for patients once they’re infected is preventing the virus spreading, which means surveillance, fast response, and building trust in communities.
“An Ebola treatment centre isn’t enough,” Trish Newport, emergency programme manager at MSF, who is based in Congo, said. “An Ebola treatment centre is the end of the line.”

Treatment capacity has expanded from only a handful of beds early in the outbreak to more than 1,700 across 50 treatment centers, with plans to exceed 2 000, according to the WHO.
Earlier in the outbreak, dozens of health workers became infected while treating patients outside specialised Ebola centres, where shortages of protective equipment, training and infection-control measures left staff exposed. About 254 health workers have since been infected and 50 have died.
Responders should be able to swarm a place when its first few infections appear, tracing contacts, disinfecting homes and engaging communities before transmission takes off, Newport said. Instead, organisations stretched across dozens of hotspots often don’t have the people or time.
“Putting out small fires isn’t possible,” she said. “And you end up with massive fires everywhere.”
This gap is visible in North Kivu, where on 2 October only seven of 30 identified households were decontaminated, due to community resistance and shortages of teams and transport.
Cases there jumped 84% last month, government reports show. MSF said on 3 October that the virus is spreading “like wildfire” in North Kivu.
When Newport arrived in Mongbwalu in July, inexperienced workers were faced with patients who often sought help only when gravely ill. As many as 20 people were dying in the community each day.
Weeks later, some 300 workers had been trained, patients were arriving earlier and deaths had fallen sharply.
Read: Ebola spreads to seventh Congo province after long-distance trip
Then Newport travelled to Bambu, about 15 miles to the southeast. What she found looked like Mongbwalu weeks earlier: inexperienced staff, patients arriving desperately late and as many as 15 people dying in the community each day.
“Every area is like a separate outbreak,” she said. “But all connected.”
The response is increasingly being pushed outward from large treatment centers and closer to villages. Thousands of community workers are going door-to-door, asking families about illnesses and deaths, identifying contacts and directing suspected cases for testing.
On 12 September alone, teams conducted almost 32 000 household visits in Ituri and North Kivu.
Congo’s response plan aims eventually to mobilise close to 71,000 community workers, according to the Africa Centres for Disease Control and Prevention.
One goal is to identify at least 50 contacts for every confirmed infection, allowing exposed people to be followed before they become sick and potentially spread the virus further. The response currently remains far from that goal. Congo reached 73% of the contacts already on its lists on 2 October – and only 60% in North Kivu.
Africa CDC estimates those lists contain less than a quarter of the contacts that would be expected from known cases. Almost 80% of new infections are being detected among people who weren’t already being followed, the agency said on 1 October.
Read: Congo Ebola responders stay on strike as Africa CDC pushes to resolve pay dispute
The virus is moving through a region that has been shaped by cross-border trade, conflict and mass displacement. Millions of people have been uprooted in eastern Congo, sometimes repeatedly.
In late September, fighting in Ituri caused thousands of people to leave their homes, including more than 3 000 who fled a camp housing displaced people. An Ebola transit center at the abandoned camp later burned down.
Aid organisations suspended movements in some areas, and the violence delayed laboratory samples and disrupted transfers of confirmed patients for treatment. Two people involved in the Ebola response were killed in North Kivu last month, according to the UN.
The outbreak has already crossed international borders. Uganda recorded imported infections and subsequent cases among contacts and health workers, while an infected traveller was diagnosed in France.
Aid workers who contracted Ebola in Congo have been medically evacuated to Germany and the Netherlands for treatment.
Continued transmission near Congo’s borders raises the risk of further spread into neighbouring countries, including the Central African Republic, Republic of Congo and South Sudan, Africa CDC has warned.
Neighboring countries are strengthening surveillance and laboratory capacity, but some start from a much weaker base. South Sudan’s health infrastructure, battered by decades of conflict, is “among the lowest on earth,” said Samantha Nutt, founder of the humanitarian organisation War Child Canada.
“Once it hits South Sudan, then it’s going to be really, really challenging.”
Ebola response faces funding shortfalls
Congo’s new six-month response plan calls for $1.3 billion. International commitments to fight Ebola have now reached about $2.9 billion following a pledging meeting in New York on 23 September .
The challenge is turning those pledges into work on the ground: Africa CDC said they need to be rapidly converted into disbursements, implementation and results. Some workers have gone unpaid, contributing to strikes that have hindered parts of the response.
Before the outbreak, US aid cuts had already disrupted programmes supporting community surveillance, specimen transport and health facilities in eastern Congo.
The International Rescue Committee, for example, had cut 60% of its health sites in Congo; in Bunia, where Sebushishe now works, only two of five primary-care sites it had supported remained open. WHO, meanwhile, froze hiring, laid off staff and cut emergency spending after losing US funding.
The Trump administration disputes that its restructuring weakened the Ebola response, and has mounted a major emergency effort since the outbreak was detected. The US announced a new $267 million commitment on 23 September, bringing its health and humanitarian support for the outbreak to $887 million.
Read: Ebola deaths double in two weeks as WHO warns virus is outrunning response
That money will expand treatment units, surveillance, contact tracing and burial teams. But emergency funding can’t instantly rebuild lost capacity or produce the experienced workers needed to turn those dollars into an effective response.
“You can pour money to get some of the commodities, but actually having trained teams to go and do this, who can use the equipment and be safe and do it in an effective way is a big limiter,” MSF’s Falconer said.

There are signs of progress. Africa CDC said October 1 that seven affected health zones had gone more than 42 days without new cases.
Ebola’s maximum incubation period is 21 days, making each three-week stretch without a new infection an important marker of progress.
But 45 health zones have reported infections within the past three weeks.
Deaths fall but surveillance gaps remain
Deaths are beginning to fall. Reported deaths declined 29% in September from August. But determining to what extent transmission has really declined remains difficult. Insecurity and community resistance have disrupted surveillance in several hotspots, Africa CDC said.
Deborah Birx, who led the US government’s global AIDS programme and later coordinated the White House’s Covid response, said she is optimistic the epidemic is declining, but would watch deaths closely because case counts can be distorted by delays in detecting and reporting infections.
“The one thing that usually is constant is death and the date of death,” Birx said. If the epidemic really is receding, she said, the slope of deaths should begin falling substantially over the next several weeks.
Rwampara, on the outskirts of Bunia, became one of the outbreak’s biggest early hotspots, recording more than 1,000 infections. Its experience also shows how rebuilding trust can change the trajectory of the response.
In May, fear and misinformation were so intense that two Ebola treatment tents were set ablaze with six patients inside. Medical aid group Alima and other responders worked with local health workers and community leaders to understand why people were afraid of ambulances, isolation and treatment centres.
Monigi, Democratic Republic of Congo – 2 June: A worker wearing protective equipment visits a patient in an isolation unit an Ebola treatment centre. Image: Daniel Buuma/Getty Images
“It required very intensive work, every day,” Carlotta Pianigiani, emergency department manager at Alima, said. Over several weeks, communities began raising alerts themselves and patients arrived for treatment earlier. By September, Rwampara was reporting only a handful of new cases a day.
But experts said that they are still only fighting the fires as they emerge, and don’t have enough staff or resources to get ahead of the crisis by identifying new clusters of cases and handling them before they become new outbreaks.
“There is a limit to how quickly experienced Ebola staff can be multiplied,” Pianigiani said. “The epidemic can geographically expand faster than specialised response capacity can be deployed.”
© 2026 Bloomberg

